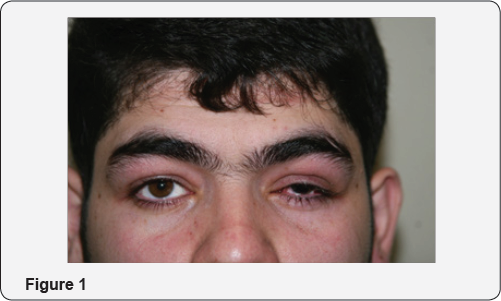
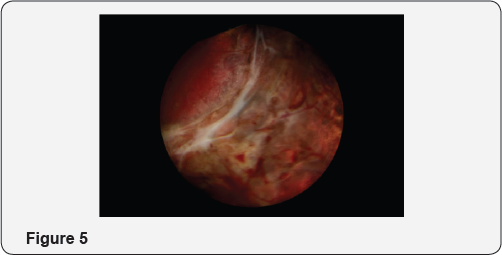
A 22-year- old man referred to the emergency ward because of vision loss in his right eye five days after bilateral lower lid blepharoplasty, his right eye showed ciliary injection, cornea showed mild edema and anterior chamber showed 4+cells and faint hypopyon in slit lamp examination, There was severe chemosis, without any site of laceration. However, fundus examination showed severe fibrinous reaction and vitritis. (Figures 1-5 are related to the post-operative status.)
Based on the diagnosis of undetermined uveitis the patient underwent diagnostic vitrectomy, interestingly there was a site of laceration in the posterior fundus, leading to peritomy and its repair associated with severe vitreous inflammation and retinal necrosis and vasculitis. The patient underwent pars plana vitrectomy associated with intra vitreal antibiotic injection and silicone oil injection; the culture of the vitreous documented staphylococcus aurous in the vitreous sample. This rare complication has been rarely described in the literature [1,2].
Although rare, doing blepharoplasty a common cosmetic
in inexperienced hand could lead to a severe devastating intra ocular
complication.
For more Open Access
Journals in Juniper Publishers please
click on: https://juniperpublishers.com
For more articles
in JOJ Ophthalmology (JOJO) please click
on: https://juniperpublishers.com/jojo/index.php
For more about juniper publishers please click on:
https://www.juniperpublishersgroup.com/
Pediatric Cavernous Sinus Syndrome as the Initial Presentation of Intracranial Germinoma: A Case Report-Juniper Publishers
8-year girl complained of diplopia and her right eye presented ptosis, supraduction, abduction deficit, slight esotropia, and corneal hypoesthesia. Visual acuity was 20/20 in both eyes. Pupillary light reflex showed full, fast constriction and afferent pupillary defect was negative. No optic disc abnormalities were observed and indicated cavernous sinus syndrome. A brain magnetic resonance imaging indicated a tumor lesion from the sellaturcica to the suprasellar region and advancing into the right cavernous sinus, compressing the optic chiasm. Tumor biopsy was performed. Histo pathological examination led to a diagnosis of intracranial germinoma. Intracranial germinoma manifest hypopituitarism and bitemporal hemianopsia but in this case, intracranial germinoma manifesting as cavernous sinus syndrome initially. Cavernous sinus syndrome represents highly in adults and pediatric cases are rare. Malignant lymphoma and Trosa-Hunt syndrome were occasionally reported as diseases causing cavernous sinus syndrome in children. But, to our knowledge, there were a few reports of intracranial germinoma. Although it is very rare, germinoma should be kept in mind as a disease which causes cavernous sinus syndrome in children.
8-year-old girl complained of diplopia from April
2006, and started tilting her head to see things. Intermittent ptosis of
the right eye appeared in May. Because right eye movement disorder was
noted, she initially visited our department on October. The visual
acuity was 20/20 in both eyes, the light reaction was complete and
rapid, and relative afferent pupillary defect (RAPD) was negative.
Ptosis of the right eye was noted. The pupil diameters were 4.6 and
3.7mm on the right and left sides in a bright room, respectively, and
4.6 and 5.7mm in a dark room, respectively, showing laterality. The
pupil diameter after a cocaine eye drop test were 4.5 and 5.7mm in a
bright room, respectively, being judged as positive for the test.
Regarding eye movement, impairment of abduction and supraduction, mild
impairment of adduction, and infraduction disorder of the right eye were
observed, and corneal sensory reflex of the right eye was reduced. No
abnormality was noted in the anterior segment of the eye, optic media,
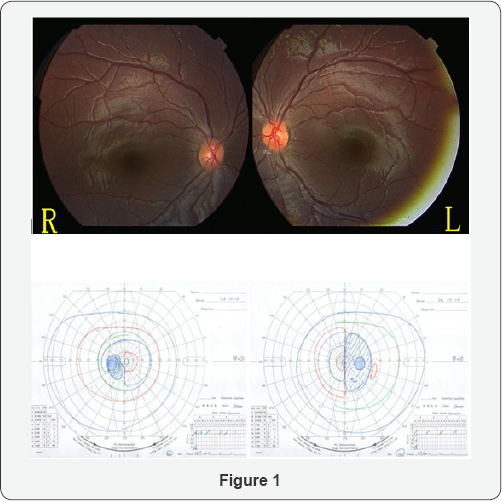
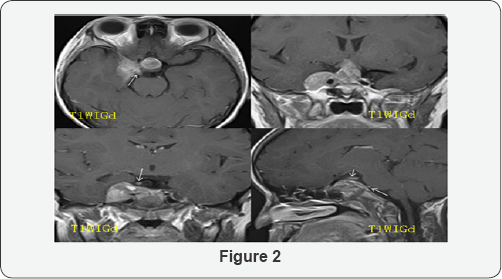
or fundus.Bitempolal hemianopia in visual field was observed (Figure 1). On brain magnetic resonance imaging (MRI) performed (Figure 2),
a mass lesion advancing from inside the sellaturcica to the supra
sellar region and right cavernous sinus was observed. Contrast
enhancement of the tumor continuous from the right cavernous sinus was
observed, and it advanced along the oculomotor and abducens nerves, the
serum human chorionic gonad otropin-β (hCG-β) level was high suggesting
germ cell tumor. Regarding the systemic condition, panhypopituitarism
was present, and hormone replacement therapy was initiated. Tumor biopsy
was scheduled but it was postponed by her family. The visual acuity of
the left eye decreased to 20/50 in February 2007, and impairment of
supraduction of the right eye aggravated. On MRI performed in the same
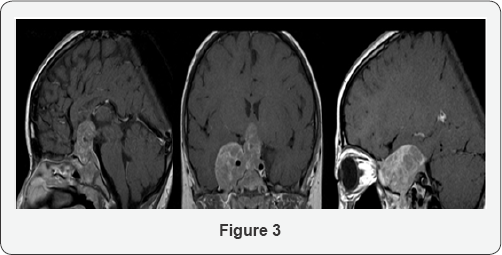
period (Figure 3),
compression of the chiasma became stronger in the suprasellar region.
On the right side, the tumor advanced along the orbital apex and
trigeminal nerve. Tumor biopsy by craniotomy was performed on March 6,
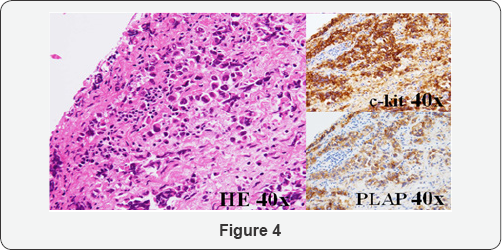
2007. Solitary appearance of large cells containing bright and wide
cytoplasm was observed on histopathological examination (Figure 4),
and cells were positive for placental alkaline phosphatase (PLAP) and
c-kit on immunostaining. Based on these findings, the tumor was
diagnosed as intracranial germinoma. Radiotherapy and chemotherapy were
immediately performed, and the tumor shrank. On follow-up in July, the
visual acuity became 20/20 in both eyes, and the tumor has not recurred
for 8 years.
In the present patient, diplopia and ptosis were the initial symptoms and the features of cavernous sinus syndrome complicated by Horner's syndrome were observed. These clinical findings were consistent with the mass lesion advancing from inside the sellaturcica to the suprasellar region and right cavernous sinus observed on MRI. To our knowledge, only 3 cases [1-3], of intracranial germinoma causing cavernous sinus syndrome as the initial symptoms. In these 3 cases, the tumor was heterogeneously enhanced with gadolinium on MRI and Serum or cerebrospinal fluid hCG-β was positive.One case is children [1]. 11-year-old girl presented of left 6th cranial nerve Palsty without visual field defect. Her head MRI showed a mass mainly located in the left cavernous sinus. First biopsy want clearly histlogycal evidence of tumor cells. Intracranial germinoma was diagnosed by second biopsy five month later. Retrospective analysis of the first specimen revealed a few cells positive for c-kit immune histo chemical stain. Thus c-kit is useful for the differential diagnosis and might have resulted in early diagnosis at the first exploration. Present case test of c-kit, hCG-β and PLAP were positive in serum or cerebro spinal fluid, so we could suspect for intracranial germinoma.
Intracranial germinoma accounts for 15% of pediatric
tumor cases and it is higher in Japan than in the other western
countries (3-4%) [4].
It arises in the pineal body and suprasellar regions and induces
various symptoms. Clinical manifectation are hypopituitarism and
bitemporal hemianopsia. In this case, intracranial germinomam anifesting
as cavernous sinus syndrome initially. Most cases occuring cavernous
sinus syndrome develop in adults and pediatric cases are rare. Malignant
lymphoma [5,6] and Trosa-Hunt syndrome [7-9]
were occasionally reported as diseases causing cavernous sinus syndrome
in children. Although it is very rare, intracranial germinoma should be
kept in mind as a disease which causes cavernous sinus syndrome in
children.
For more Open Access
Journals in Juniper Publishers please
click on: https://juniperpublishers.com
For more articles in JOJ Ophthalmology (JOJO) please click on: https://juniperpublishers.com/jojo/index.php
For more about juniper publishers please click on:
https://www.juniperpublishersgroup.com/
Triamacinolone Acetonide Versus Bevacizumab in Treatment of Neovascular Age Related Macular Degeneration-Juniper Publishers
Purpose: To evaluate the effects of intravitreal triamacinolone acetonide (IVTA) and bevacizumab injection on visual acuity, electro physiologic response and foveal thickness of patients with neo vascular age related macular degeneration (CNVs).
Methods: The study included three groups. Group 1 included fifty eyes (50 patients) with progressive occult or predominately occult sub foveal choroidal neovascularization treated with intravitreal injection of trimacinolone acetonide. Group 2 included another fifty eyes (50 patients) with progressive macular degeneration of occult or predominately occult sub foveal choroidal neovascularization treated with intravitreal bevacizumab. The patients is followed up every month by bio microscopy, optical coherence tomography (OCT), photography, fluoresce in angiography, Ganzfeld full field electro retinogram(F-ERG), multifocal electro retinogram (MF-ERG) and determination of best corrected visual acuity (BCVA). Group 3 (control group) included 50eyes (50 patients) with neo vascular age related macular degeneration who did not receive treatment for macular degeneration.
Results: Apparent improvement of morphological and functional characteristics were observed in 40/50 eyes after one month after first injection in group1, and in 45/50 in group 2. The mean±SD visual acuity improved significantly (p=0.003) from (0.12 ±0.19 to 0.35±0.25) in group1 and from 0.13±0.2 to 0.40±0.28 in group 2. Visual acuity was highest 1-2 month after intravitreal injection. Central macular thickness decreased from 325±50^m to 275±40^m at one month after first injection in group 1 and decreased from 320±53^m to 255±41^m in group 2 while in control group, there is statistically insignificant increase of the central thickness. The average amplitude of central macular ring of MFERG was improved from 25.5±5.8nv to 31±8.9nv in group 1 and from 26.6±6.1nv to 33±9.9nv in group 2, while no changes in F-ERG response. Intraocular pressure increased significantly (p=0.009) from 14±2.5mmHg to maximal 23±7.6mmHg in group 1. Intraocular pressure decreased significantly (p=0.006) to 16±2mmHg at the end of follow up while in group 2, there was no increase in intraocular pressure. No other serious drug related adverse events (endophthalmitis, retinal detachment, cataract or proliferative vitreo retinopathy) observed during the course of the study in groups 1, 2. In control group, visual acuity, central foveal thickness and function did not change significantly during follow up period (p=0.6, p=0.4, p=0.1 respectively).
Conclusion: Intravitreal injection of trimacinolone acetonide may transiently stabilize or improve visual acuity in some patients with progressive neo vascular age related macular degeneration. Intravitreal injection of bevacizumab led to a more visual improvement than IVTA in treatment CNVs. MFERG had an important role in describing the effect of treatment on retinal function. Intravitreal injection improved MFERG macular function responses with little insignificant change in F-ERG.
Keywords: Electroretinogram; Optical coherence tomography; Choroid neovascularization; Avastin; Triamacinolone acetate
None of the present treatment decreases the loss of vision on the central 35° of the retina in macular degeneration. Neovascular age related macular degeneration is a common reason for irreversible reduction and loss of vision in the world [1] . Triamacinolone acetonide is one of the first drugs used for the management of age related choroidal neo vascularization [2] . Triamacinolone acetonide stabilizes blood retinal barrier, decreases the permeability and inflammation, increases the diffusion and reduces vascular endothelial growth factor [3]. Vascular endothelial growth factor (VEGF) plays important role in AMD pathogenesis [4]. Bevacizumab is humanized antibody to human vascular endothelium growth factor (VEGF) which combines to VEGF and hinders it from attachment to its receptors [5]. Electro retinogram of neo vascular macular degeneration gives information about the treatment safety. MF-ERG represents the photopic retinal response to a rapidly changing stimulus on the central 35° of the retina [6]. Neovascular age related macular degeneration decreases the central peak amplitude which is altered by subretinal fluid [7]. MF-ERG is used to monitor the localized change after treatment. Full field ERG response reflects general retinal electrical response and gives information about treatment toxicity [6,7]. The aim of the study was to evaluate and compare the effects of triamacinolone acetonide and bevacizumab on visual acuity and retinal thickness in neovascular age related macular degeneration patients and to study the effects of triamacinolone acetonide and bevacizumab on the retinal function.
This study was carried out on patients attending the Outpatient's Clinic of Mansoura Ophthalmic Center during the period from February 2012 to December 2015. One hundred and fifty patients (150) with neovascular age related macular degeneration were included in the study.
The patients were divided into three group:
a) Group 1: Included progressive occult subfoveal choroidal neovascularization patients who received intravitreal injection of triamcinolone acetonide.
b) Group 2: Included occult subfoveal choroidal neovascularization patients who received intravitreal injection of bevacizumab.
c) Group 3 (control group): Included neovascular age related macular degeneration patients who refused intravitreal injection.
Included patients with classic type of neovascular age related macular degeneration and any other ophthalmological. All patients were examined on the first day after injection, in first week, then every month for 6 months. A repeated injection was performed if there were activity of choroidal neovascularization (CNV). Intra-retinal and sub-retinal fluid accumulation, new intra-retinal and sub-retinal hemorrhage and CNVs growth were signs of CNVs activity. Re-treatment was done if there were signs of CNV activity or decreasing visual acuity. At baseline of the study and at monthly intervals, all patients underwent a routine ophthalmological examination. Goldman applanation tonometry, direct and indirect ophthalmology, optical coherence tomography (OCT), and electroretinogram (ERG) were done. Fluorescein angiography was done using Topcon Corporation 2000, TRC, 50Ix, Japan. Fluorescein angiography was performed for all patients at beginning and after 3months and 6 months.
OCT was done with Topcon, 3 dimensional OCT-1000 (Topcon Corporation, Tokyo, Japan). Internal fixation was chosen because of better reproducibility. It scanned a cube of 6x6mm length. Central macular thickness of a circular 1-mm radius area around the fovea was calculated.
Full field ERG and MF-ERG were recorded using Roland Consult, (Germany system). ERG was done according to ISCEV standard [8]. After topical corneal anesthesia (Benoxinate hydrochloride 4%), positive electrode (Dawson, Trick and litzkow (DTL) electrode) was placed just contact with corneal limbus, ground electrode was installed on the forehead and negative electrode was placed near orbital rim temporary. The recording was monocular.
The test was started and recorded in 5 steps, scotopic rod response, scotopic combined response, oscillatory potential then light adaptation for 10 minute then photopic cone response and flicker response recording.
Patients were positioned 30cm from the stimulus monitor. Stimulus clarity was adjusted by over-refraction. Each hexagon was temporally modulated between light and dark according to binary m-squence [9,10]. Patients fixated a spot in the center of the stimulus. The results of two 8-minute recordings were averaged to improve the signal to noise ratio.
In group 1, 25mg of crystalline triamacinolone acetonide (Volona A, Bristol-Myers-Squibb, Munich, Germany, containing 40mg of triamacinolone acetonide in 1ml) was injected intravitreal. The injection of 25mg of crystalline triamacinolone acetonide was performed using sharp 27-gauge needle in inferio-temporal quadrant 3.5mm from limbus.Then antibiotic ointment was applied.
All patients in group 2 received Intravitreal injection of 1.25mg/0.05 of bevacizumab. A total of 0.05ml Bevacizumab was injected into vitrous cavity 3.5mm from limbus in inferotemporal quadrant using 30 gauge needles. Postoperative antibiotics were used and a light patch was placed. The eye patch is removed the next day.
Statistical analysis was performed using soft ware (SPSS WIN Version11.5, SPSS Inc, Chicago). Non parametric Wilcoxon test was applied for comparison. Spearman rank test and linear correlation analysis were used in order to evaluate the correlation with changes of MFERG, changes of OCT and best correct visual acuity. Significance was set at p=0.05 (2-tailed) for all statistical tests.
The study included one hundred and fifty (150)
patients (one hundred and fifty eyes). The patients were divided into
three groups. Group 1 included fifty eyes (50) of fifty patients (50)
with progressive occult or predominately occult subfoveal choroidal
neovascularization who received one or more than one of intravitreal
injection of 25mg of triamcinolone acetonide, Mean age was 60±8.6years
,ranged (55 -75 years old). Group 2 included another fifty eyes (50) of
fifty patients with progressive occult or predominately occult sub
foveal choroidal neovascularization) who received one or more than one
of intravitreal injection of 1.25mg/0.05ml of bevacizumab. The Mean age
was 62±6.9 years, ranged (58-74 years). Group 3 (Control group) included
fifty eyes (50) of fifty patients (50) (with neovascular age related
macular but did not receive intravitreal injection of tri amcinolone
acetonide for this disease after explanation the importance of treatment
for visual acuity and CNVs. The Mean age was 61 ±7.9 years, ranged
(58-74 years). There was no significant difference between groups. In
group 1, Ten (10) patients received a second intravitreal injection of
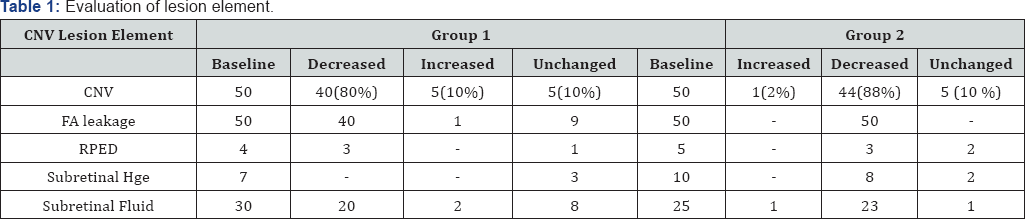
25mg of triamcinolone acetonide. According to flourescein angiography,
group 1 were further divided into subgroups with occult or mostly
(>50%) occult without hemorrhage (n=40, 80%), subgroup with
sub-retinal hemorrhage (n=7, 14%) and subgroups with retinal pigment
detachment (n=4, 8%). While in group 2, occult CNV without haemorrhage
was presented in 35 eyes (70%), with haemorrhage was present in 10 eyes
(20%) and retinal pigment detachment was found in 5 eyes (10%) ( Table1).
All three subgroups did not vary significantly (p=0.2) at baseline. In
control group, all subjects were having occult CNV without sub retinal
hemorrhage.
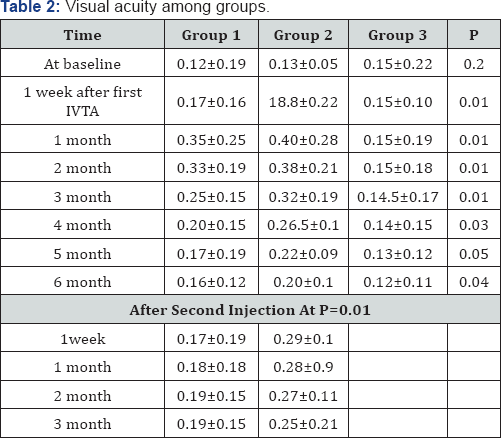
All patients complained of decreased visions which were diagnosed by ophthalmologic examination within three months before IVTA. The mean VA at baseline in group 1, group 2 and control Group (0.12±0.19, 0.13±0.05 and 0.14±0.22) respectively. (Range from finger counting to 0.3 in group 1, from finger count to 0. 32 in group 2 and from finger counting to 0.5 in control group. For the Group 1 and Group 2, mean VA increased significantly (p=0.003) after first injection to maximum 0.35±0.25 during the follow up period (Table 2). The maximum postoperative VA was detected 1-2 months after the injection. The increase in VA was statistically significant in 1st month (p=0.003) and 2nd month (p=0.004) after the injection. The preoperative visual acuity and postoperative visual acuity achieved at the end of the follow up period did not differ significantly (p=0.2) in group 1 while in group 2, there is statistically significant difference between VA at the baseline and VA at the end. In group 1, Visual acuity significantly decreased towards the end of the follow up period, parallel to a disappearance of triamacinolone acetate crystals out of vitreous cavity. In group 1, after 1 month, 40eyes (80%) gained in visual acuity and 4eyes (8%) lost visual acuity. Visual acuity was unchanged for 6 eyes (12%). While, in group 2, 45 eyes (90%) gained in visual acuity. There were no significant correlation between postoperative visual acuity and postoperative change in visual acuity (p=0.6). For three subgroups, there were significant difference in gain in visual acuity (p=0.04). Ten eyes received second injection three months after first injection, visual acuity increased in eight eyes about one month after the re-injection and declined again after about 3 month in group 1 while in group 2, fifteen eyes received second injection after 2 months, and fourteen eyes of fifteen improved after reinjection.
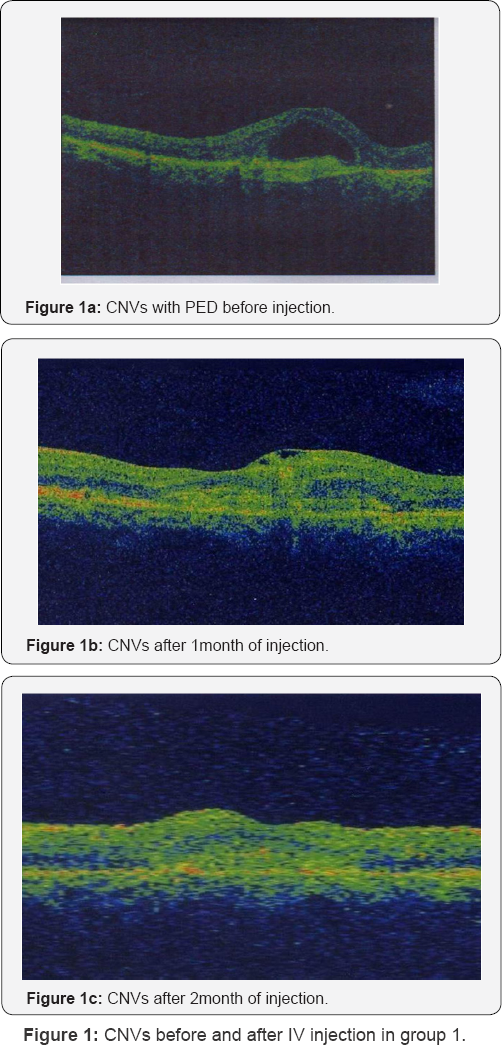
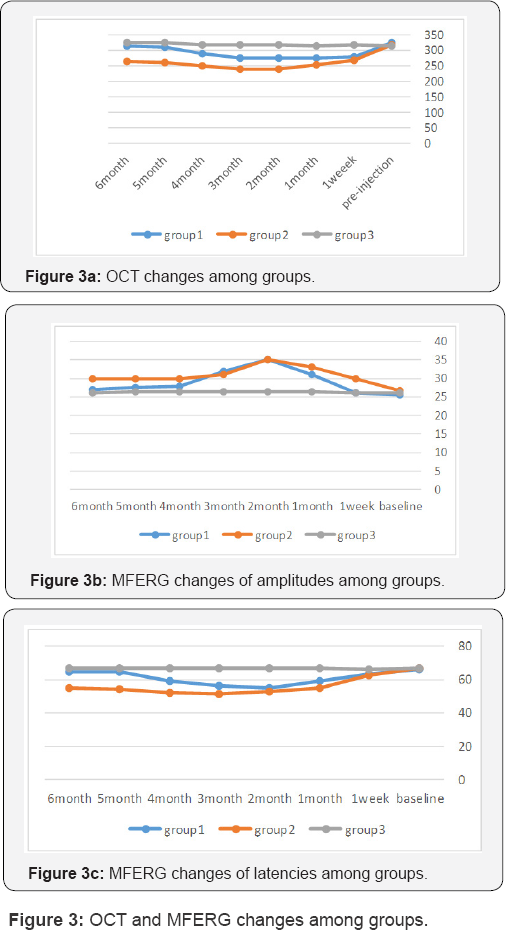
For group 1, Central subfield OCT thickness was
325±50μm at baseline. The central subfield OCT thickness decreased to
280±55μm at one week and 275± 40μm at one month (Table 3, Figure 1).
In group 2, central subfield OCT thickness was 320±53μm at baseline.
The Central subfield OCT thickness decreased to 270± 40μm at one week
and 255±41μm at one month
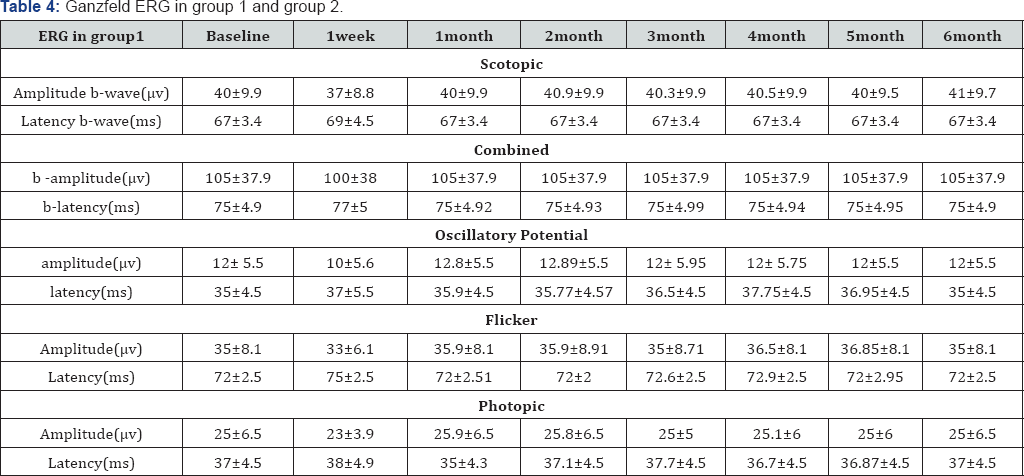
F-ERG data is presented in (Table 4).
No significant worsening of FERG response was observed during follow up
period in the three groups. Most of the values were within the limits
normal variation. For most subjects retested one month with F-ERG, the
amplitude returned to baseline after a slight decrease in scotopic and
photopic amplitudes at one week. For all subjects who was received
either triamacinolone acetate or bevacizumab had an essentially stable
F-ERG.
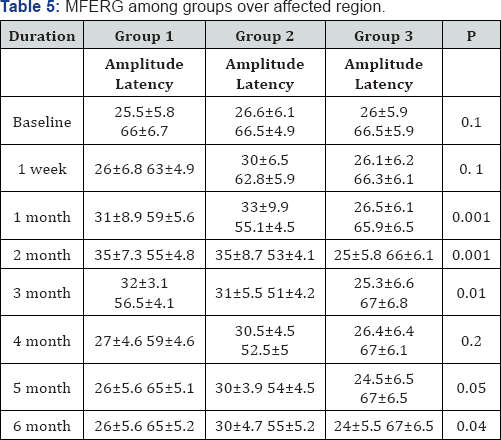
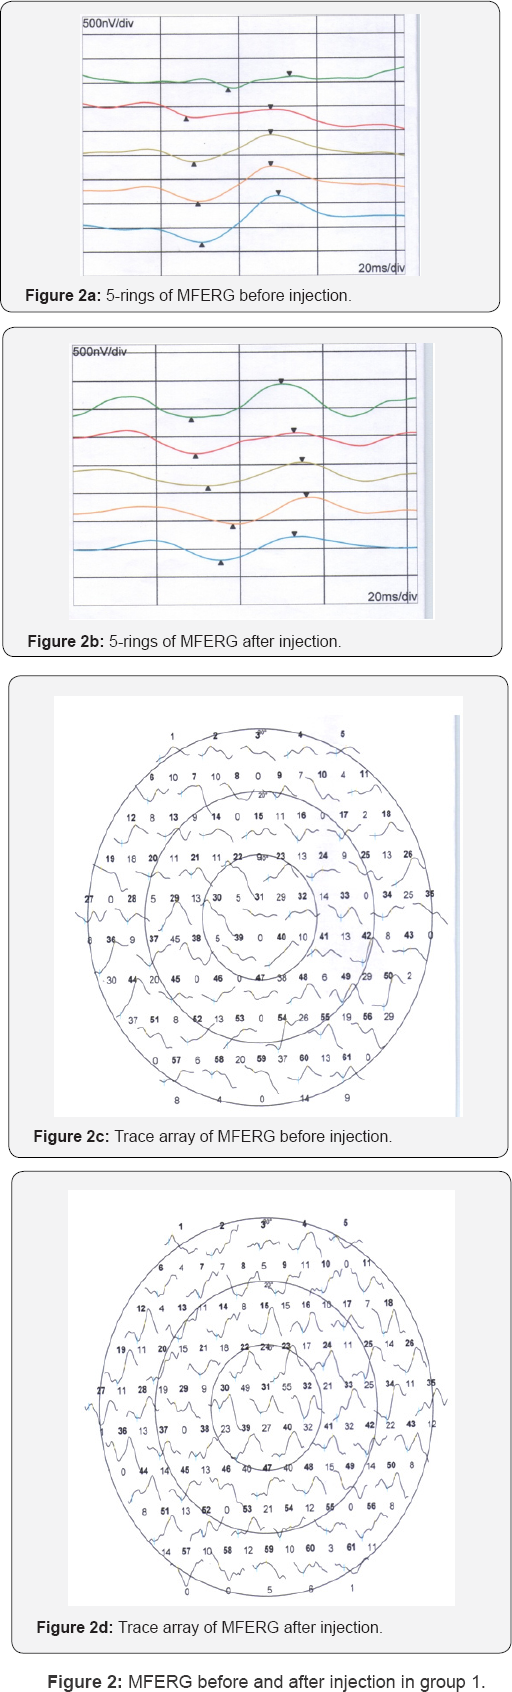
In most cases, there was improvement at one week, one month and two months of IVTA, then return to baseline value at 3 months (Table 5, Figure 2 & 3). In group 2, there was increase in amplitude and decrease in latency reach the maximum after 2 months.
In group 1, IOP increased significantly (p=0.005) from 14.5±2.5mmHg at baseline of the study to a mean maximal value of 20±5.6mmHg again decreased significantly to 16.5mm Hg at 6 months after IVTA at p=0.001. IOP measurements at the end were slightly and significantly (P=0.05) higher. During the study, IOP was higher than 22mmHg in 30 eyes (60%). In those patients, IOP normalized by topical anti-glaucomatous drugs. Optic nerve damage was not detected. While in group 2, there was no case with increase in intraocular pressure. With respect to other complication of IVTA, three cases of cataract were detected in group 1, while no case of cataract was observed in group 2. No postoperative infectious endophthalimitis, rhegmatogenous retinal detachment or proliferative vitreo-retinopathy was detected in groups 1 and group 2.
While, classic type of subfoveal neovascularization, photodynamic therapy with verteporfin stabilizes or increases visual acuity. Photodynamic therapy for occult subfoveal neovascularization is unsuccessful [11,12]. Steroids have antiinflammatory, antiangiogenic, antifibrotic and antipermeability properties, which contribute to stabilization of the blood- retina barrier [13] Penfold et al. [14,15] Chella et al. [16], injected trimacinolone intraviteal to treat exudative macular degeneration. Additionally, Danis et al. [17], detected a beneficial effect of trimacinolone in the study group compared with control group. Also, Ranson et al. [18], treated recurrent subfoveal neovascularization after laser treatment by IVTA. Chella et al. [16] evaluated the efficacy of intravitreal of trimacinolone for one and half year in exudative age related macular degeneration. They reported that a single intravitreal injection of 4mg of trimacinoloneacetate was helpful in treatment of exudative age related macular degeneration. In this study (in group 1), there was increase in visual acuity, reduction of fluorescein angiography leakage, reduction central macular thickness and increase in amplitude of MFERG with reduction of implicit time in 40 eyes of 50eyes (80%) within 2 months. Ten eyes of 40 eyes (25%) receive another intravitreal injection after 3 months (after beginning of reduction of visual acuity with increase macular thickness, reduction of amplitude of MFERG and increase implicit time). There was improvement of six of ten eyes (60%).
There was correlation between visual acuity and central macular thickness (p=0.008, R=0.5) and visual acuity and MFERG amplitude (P=0.006, R=0.55). Also, there was significant correlation between central macular thickness and MFERG amplitude (P=0.001, R=0.65) in group 1. In this study, we injected high dose of triamcinolone acetate intravitreal in group 1, because the results of previous studies were not clear; Jonas et al found significant increase in visual acuity after intravitreal injection of 25mg of trimacinolone acetate [19,20]. while Gillies et al. [21], reported no effect of 4mg of intravitreal injection of trimacinolone acetate on the development of sever visual loss during one year follow up. The Causes for the difference between studies may be the amount of injected trimacinolone acetate Second cause for difference between studies may be related to the effect of development of cataract on vision. Other cause for discrepancy between this study and investigation of Gillies et al. [21] may be that their study included classic subfoveal neovascularization that had a worse prognosis than occult choroidal neovascularization.
There was significant elevation in intraocular pressure in group 1 compared with other groups. There was 30 eyes (60%) had increased intraocular pressure. All cases were controlled with medical anti-glaucomatous treatment. Various studies have reported increase of IOP ranging from11-30% of subjects following IVTA [17,19,22] None of patients had been shown infectious endophthalmitis, rhgmatogenous retinal detachment , or proliferative vitreo retinopathy in this study .
Jonas et al. [19] found the reduction of visual acuity started 4-5 months after initial increase in visual acuity two months after injection. Similarly, in the present study after initial increase of vision two month after injection, visual performance started to decrease again. This may be result from resolving of trimacinolone acetate crystals Vascular endothelial growth factor (VEGF) plays an important role in the pathogenesis of AMD 22 Intravitreal bevacizumab injection was reported to be effective for treatment exudative AMD. Bevacizumab inhibit VEGF, decrease angiogenesis and decrease vascular permeability. [23-25].
In group 2, there were increase in visual acuity,
reduction in retinal thickness and improvement of electrophysiological
amplitudes and latencies. The improvement was slightly more significant
in group 2 than in group 1 (As seen in Table 1)
The cause for this improvement in group 2 more than group 2 is that
triamcinolone exerted its antiangiogenic effect by enhancing endostatin
expression rather than suppressing VEGF expression [26]. While bevacizumab decrease angiogenesis by decreasing VEGF expression and enhancing endostatin [27].
There was correlation between visual acuity and central macular
thickness (p=0.006, R=0.55) and visual acuity and MFERG amplitude
(P=0.005, R=0.65). Also, there was significant correlation between
central macular thickness and MFERG amplitude (P=0.003, R=0.6) in group
2. Similarly, Rosenfeld et al reported that intravitreal injection of
bevacizumab cause marked decrease in retinal thickness without toxicity [28]. Ahmadieh et al. observed improvement of vision and reduction of thickness after bevacizumab [29]. Also, Falkenstein et al showed that primary bevacizumab therapy resulted in significantly visual improvement [30]. The bevacizumab preparation is unpreserved and contains no ingredients that are toxic to the eye [28].
Intravitreal bevacizumab is well tolerated in the majority of patients.
In this study, there were no complications in group 2. Only
subconjuctival heamorrhage in two cases which resolved within a week.
While, Ahmadieh et al. [29]. Observed one case with pigment epithelial detachment without any cases of endophalmitis or sub-conjuctival haemorrhage [29]. Also, Cleary et al. [30].
Found endophthalmitis in 1 of 112 eyes, submacular hemorrhage in 3 of
112 eyes and retinal pigment epithelial tears in 3 of112 eyes. Ronan et
al. [31],
and Avery said that the presence of pigment epithelial detachment was
risk factor for retinal pigment epithelial tear after IVB injection [32].
The limitations of this study were the method of measuring visual
acuity. Instead of the charts used for the Early Treatment Diabetic
Retinopathy [33],
visual acuity was determined using Snellen charts. But, the same method
was used to three groups. Other limitation of this study was limited
follow up and limited number of the patients, the relatively high dose
of trimacinolone acetate injected into eye. In summary, intravitreal
injection of trimacinolone acetate and bevacizumab improve visual acuity
transiently in patients with neovascular age related macular
degeneration. Furthermore, intravitreal injection caused anatomical
changes and functional improvement of MFERG. Bevacizumab gave more
favorable visual outcome and anatomical and functional improvement than
triamcinolone acetate. To stabilize visual acuity, repeated intravitreal
injection is recommended with 2-3 months apart with take care of
complication especially intraocular pressure in cases of IVTA.
For more Open Access
Journals in Juniper Publishers please
click on: https://juniperpublishers.com
For more articles in Journal
of Physical Fitness, Medicine & Treatment in Sports
please click on: https://juniperpublishers.com/jpfmts/index.php
For more about juniper publishers please click on: https://www.juniperpublishersgroup.com/
Monocular Optic Neuropathy: Case Unsolved-JOJ Ophthalmology
Female patient, 58 years old, unremarkable general medical and ophthalmological history, complains about pulsatile headache, with no irradiation, no specific location, and absence of nausea or vomiting. The headache would not aggravate after Valsalva maneuver and faded without medication. Also, refers vision loss in the right eye (RE) since the beginning of the headache, 10 days before. The best corrected visual acuity (BCVA) was hand movement in the (RE) and 9/10 Snellen scale in the left eye (LE). It was observed a relative afferent pupillary defect (RAPD) graded 3+, no color perception on the RE, Ishihara plates fully read in the LE, no eye movement alterations, and no facial proprioception alterations. The anterior segment had no inflammation signs and phacosclerosis was present in both eyes. Posteriorly, therewas no signs of disc inflammation, vitritis, macular or vascular alterations. Intra-ocular pressure (IOP) was 15 mmHg bilaterally.
Emergency head Computorized Tomography (CT) and Magnetic Resonance Imaging (MRI) with gadolinium were performed to rule out optic pathway lesions or neuritis. ESR, CRP, blood count were performed to exclude Giant Cell Arteritis, wich all came negative [1]. Furthermore, testing for HIV, Syphilis, Hepatitis B and C, IGRA Quantiferon-TB (Tuberculosis), ACE and urinary calcium (Sarcoidosis), ANCA PR3 and MPO (Autoimunity), HLA-B51 (Behçet's disease) and Anti-NMO Aquaporin 4 antibodies (Devic's disease) was completed, with no positive results [2]. Optic disc and macular spectral domain Ocular Computorized Tomography (sdOCT) had no acute alterations. Computorized static perimetry (CSP) was unreliable due to a high percentage of false positive and negative responses, but revealed a deep and general loss of visual sensitivity across all right visual field.
At this time, the main differential diagnosis were:
Although there was no big abdominal or heart surgery previously, an RAPD graded 3+ and deep visual loss were present [3], without optic disc edema.
The patient was not young enough to fit the diagnosis of multiple sclerosis or Devic's disease, plus, there were no lesions revealed by the MRI or neurological symptoms, but due to the profundity of visual loss [4], these options had to be considered.
No disc edema was observed, so by definition, this option was excluded [5]. The patient had no risk factors.
After exclusion of infectious possibilities, a 1Gr metilprednisone/day was administered for 3 days. After this period [6], she was medicated with oral prednisone 1mgr/Kg/ day for 2 months, and then started to halt it in a slow manner.
The patient improved greatly after 2 months. RE BCVA was 9/10, no RAPD was present, Ishihara plates were completely read and equally fast [7]. RE CSP, wich had initially a Visual Function Index of 2%, presented lastly 65%, with a medium deviation of -15.42dB and pattern stand deviation of 8.45dB. LE was considered unremarkable. sdOCT revealed RE optic disc atrophy, as the peripapillary nerve fiber layer had a thickness of 60|im, and an apparent loss of macular nerve fiber layer thickness [8]. The optic atrophy was observed at the slit lamp.
Initially, due to the absence of optic disc edema,
the options considered were posterior to the optic disc, which lead us
to think of Multiple Sclerosis and Devic's disease, but the neuro
imaging and blood testing ruled out these possibilities. After 2 months,
although RE vision had improved, an optic atrophy was evident. It's
curious as there was no optic disc edema observed throughout the
follow-up, and no occupying-space lesion was identified. Since there was
a clinical response to the steroids, ON is a possible diagnosis,
although the study was negative.
For more Open Access
Journals in Juniper Publishers please
click on: https://juniperpublishers.com
For more articles in Journal
of Physical Fitness, Medicine & Treatment in Sports
please click on: https://juniperpublishers.com/jpfmts/index.php
For more about juniper publishers please click on:
https://www.juniperpublishersgroup.com/
Hemi-Central Retinal Vein Occlusion Secondary to the Habit of Forceful Sneeze Prevention-Juniper Publishers
31 year-old man applied to the eye clinic with a complaint of silhouette in the lower paracentral visual field on his left eye. His central visual acuity was 10/10 both on his eyes. Fundus examination revealed hemi-central vein occlusion sparing the macula. A few days later widespread intra-retinal hemorhages fell into macula and visual acuity reduced dramatically. Detailed story of the patient pointed out that he had a lomber disc herniation 3 months ago at L3-L4 levels. Detailed history also showed that the patient had hypertrophic adenoids and hypertrophic nasal conc has which are under treatment by nasal decongestants. The patient did not have a heavy conditional work. But it had been speculated that powerful prevention and keeping the sneeze resulted both the herniation and hemi-central vein occlusion. Vein occlusions are common among olders but systemic disorders must be ruled out in youngers. We intended to share acute intra-ocular pressure increase as an uncommon cause for vein occlusion in this dramatic young man because systemic disease research came clean. Lomber herniation usually occurs secondary to forcing the inter-vertebral discs to high pressures that they can endure. So they can rupture and cause disc herniation. Performing valsalva maneuver by coughing, sneezing or sneeze prevention may increase pressure inside the medulla spinalis so it can result as disc herniation. This maneuver not only affects on the intervertebral discs, but also on all intra- and extra-dural structures and nerves [1]. So optic nerve head may be affected as an intra-dural component.
Hemi-central retinal vein occlusions which are classified in central retinal vein occlusion may result from hypertension, diabetes, atherosclerosis, hyper coagulable states and hypercholesterolemia. Younger patients with hemi-central retinal vein occlusion must be ruled out from diseases mentioned above. Valsalva manoeuver is the forced exhalation against a closed glottis. First described by an Italian anatomist in 17th century Antonio Maria Valsalva, it is now a well known entity amongst medical practitioners. It leads to increased intra- thoracic and intra-abdominal pressure and raised central venous pressure. It is an uncommon condition and has been reported to occur with various forms of Valsalva stress such as weight lifting, physical exercise, balloon blowing, birth labour [2]. Sneezing prevention may be accepted as a rare cause of valsalva stress. Preretinal haemorrhage caused by this sudden rise in venous pressure was first termed as Valsalva haemorrhagic retinopathy by Duane TD in 1972 [3]. Valsalva retinopathy is typically seen in young males. Sometimes it may make a fluid level which's location can be subinternal limiting membrane (ILM) or subhyaloid. Duane [3] first postulated the mechanisms for retinopathies due to distal trauma as alteration in arterial circulation (forward retinopathy), venous circulation (backward retinopathy) or to changes occurring in both systems (mixed retinopathy). Valsalva retinopathy may look like vein occlusions in appearance as spreaded intraretinal haemorrhages but transformation of valsalva retinopathy to vein occlusion related macular edema is a rare antity. Here i report a case about valsalva retinopathy which transformed to complete hemi-central vein occlusion in a week.
A 31 year-old healthy man complained about a blurry
silhouette in the lower para-central visual field in his left eye after a
powerfull sneeze prevention. Ophthalmic examination revealed bilateral
10/10 visual acuities and normal ocular tensions. Detailed examination
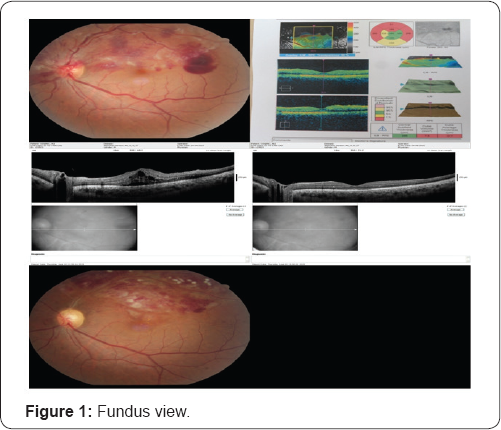
showed a hemi-central vein occlusion sparing macula in the left fundus.
There were widespread intra-retinal haemorrhages diffused in the upper
hemi- central retina and a pre-retinal and subhyaloid haemorrhage just
near the temporal macula. The fundus view is seen in Figure 1.
Questioning about heavy work conditions for probable valsalva maneuver
indicated a sneeze prevention habit. He had a lomber disc herniation at
the L3-L4 levels 3 months ago and hypertrophic adenoids and nasal
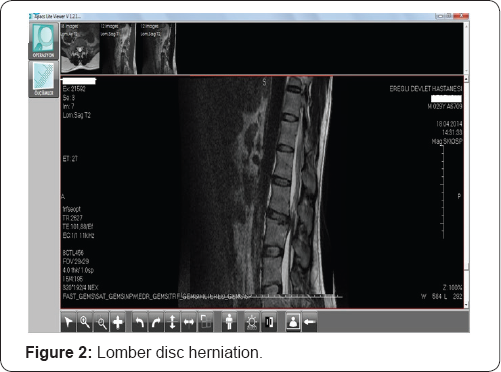
conchas which were still being treated by nasal decongestants. Lomber
disc herniation is seen in Figure 2.
Sneeze prevention habit was accused for lomber disc herniation by
neuro-surgeon. After a week of rest recommendation and conservative
management for valsalva retinopathy, the haemorrhages came to the bottom
of macula and clinical macular edema settled upon as his visual acuity
decreased to 3/10. Intravitreal bevacizumab injection was performed in
other eye center at second week and he had full visual recovery again in
two weeks time after the injection.
There were no retinal holes, tears, detachment, perivascular sheathing or snow banking at parsplana. Vein occlusions were not common among youngers so investigations including complete blood counts, clotting parameters such as antithrombin, protein c, protein s, d-dimer, factor 5, biochemical parameters such as urea, creatinine and glucose, crp, sedimentation were normal. Systemic evaluation was carried out by the physician and no abnormality was detected. We diagnosed him as hemi-central vein occlusion secondary to valsalva retinopathy. Systemic clotting abnormalities must be ruled out in hemi-central retinal vein occlusion among youngers. Disc herniation without predisposing factor and vein occlusion after sneeze prevention steered us to think about valsalva retinopathy. Intravitreal bevacizumab injection was performed and laser photocoagulation was performed for the macular edema secondary to hemi-central retinal vein occlusion. Because of the valsalva retinopathy was not limited to the pre-retinal and sub-hyaloid area, a week later the haemorrhages were spreaded widely to the macula and macular edema was settled. The visual acuity of the patient decreased to 3/10 snellen on the left and conservative treatment modality for the valsalva haemorrhagic retinopathy was replaced by the treatment of macular edema secondary to hemi-central retinal vein occlusion.
The visual acuity of the patient is 10/10 on both eyes with complete resolution of macular edema for 2 months. Ghost vessels are seen on fundus examination and retinal haemorrhages are just about to resolve. These are seen in Figure 1. Bed rest and avoiding from valsalva maneuvers were adviced for lumbar disc herniation.
Valsalva retinopathy is a unilateral or bilateral
condition which occurs by rupture of superficial retinal capillaries.
Heavy lifting, straining, coughing or vomiting may cause it. Valsalva
maneuvers typically result in superficial retinal
haemorrhages(sub-internal limiting membrane, subhyaloid) with a
predilection for the macula, but subretinal, retinal and vitreous
haemorrhages have been reported. The prognosis is variable, however
complete visual recovery is possible [4]
Some patients may develop a poor visual outcome due to the presumed
toxic effects of dense premacular haemorrhages on the retinal pigment
epithelium and/or epiretinal membrane formation. Nd-YAG laser puncture
of the posterior aspect of the vitreous may allow drainage of premacular
haemorrhage or vitrectomy may be performed in selected cases [4].
It may also managed conservatively with good outcomes. It may Valsalva
retinopathy is a self-limited condition. Recurrence of valsalva
retinopathy can be encountered if preventing any condition leading to
valsalva like stress is not succeeded [2].
Our patient did not know about the harmful effects of sneeze
prevention. A careful history is the key to the diagnosis. The prognosis
is good and patient needs to be counselled to avoid any such Valsalva
manoeuver like stress to prevent recurrence in future. Habits which are
against the physiology such as sneeze prevention may be harmful.
Patients should be careful in every physical activities which may induce
valsalva maneuver. Valsalva retinopathy may be seen as central or
hemi-central retinal vein occlusion.
For more Open Access
Journals in Juniper Publishers please
click on: https://juniperpublishers.com
For more articles in Journal
of Physical Fitness, Medicine & Treatment in Sports
please click on: https://juniperpublishers.com/jpfmts/index.php
For more about juniper publishers please click on:
https://www.juniperpublishersgroup.com/